We’ll be happy to help via online chat or at: orders@premiumbarefoot.com

Walking, Movement and Health Stories and Brands
What does orthopaedic prosthetics mean? What are the most common foot issues specialist Petr Kadlec deals with, and what’s his view on barefoot shoes? Read the interview.
Petr Kadlec is an orthotist-prosthetist who has gained hands-on experience in several prosthetics companies, where he focused on making bespoke orthopaedic aids. What does that include? Prostheses for patients after amputation, limb orthoses for children with disabilities, taking measurements for made-to-measure footwear, as well as producing orthopaedic and sensomotor insoles.
He now applies his knowledge and experience from prosthetics practice in a podiatry clinic in the Zlín Region. Here, he mainly focuses on functional assessment of the feet and gait, with the option of a comprehensive solution including custom insoles and advice on choosing the right footwear. In his work, he stays in touch with physiotherapists and doctors so that clients’ health issues are always addressed in a truly holistic way.
It’s a broad healthcare discipline that includes a whole range of sub-specialisms. An orthotist-prosthetist makes, for example, limb or trunk orthoses, prosthetic devices for patients after amputations, orthopaedic insoles, and made-to-measure orthopaedic footwear and so on. Aids are made either individually to measure, or the aids provided are off-the-shelf. Of course, it all depends on the specific health issue and the needs of each client.

It’s very individual, depending on the type of aid needed and the client’s health status. If a client needs a simpler aid, such as an off-the-shelf insole, a heel lift, a toe separator, etc., then they can come to orthopaedic prosthetics at any time without any referral from a doctor and they will pay for the aid themselves.
However, most aids are custom-made and very expensive, and without a referral from a specialist doctor the client can’t do without one – it’s about issuing a prescription or request form. The speciality of the prescribing doctor is always determined by the specific type of aid. Even with more complex aids, though, you won’t go wrong by visiting an orthopaedic prosthetics clinic directly and asking there about the correct procedure.
You’ll learn lots of important information (which doctor you should see, what paperwork you need to bring, how the approval process with the health insurance company will work, how the aid will be made, and so on).
It’s a medical device made specifically to measure for an individual client, and it can’t simply be used for someone else. Measurements are taken individually depending on the device. This might involve plaster casting, scanning, fine-tuning the device to fit, heating and moulding adjustments, and so on.

A big one. With most medical aids, the reality is that on their own they solve almost nothing. Put simply, they can be a good servant but a bad master. Any aid needs to be supported with proper education, ongoing check-ups and, above all, regular exercises under the guidance of a physiotherapist.
In terms of the timeline: a doctor prescribes the aid, the prosthetist helps the client with approval from the health insurance company, arranges production and then training on how to use it—but in the end, it’s the physiotherapist who spends the most time with the client. They guide the client, do the exercises with them, discuss everything around the health condition and the aid, and try to make the most of both the client’s potential and the aid provided.
In practice, what has worked well for me is staying in contact with the physiotherapist from the very first consultation with the client. This approach often prevents misunderstandings and, before production even begins, confirms that the planned aid will align with the long-term goal of the therapy.
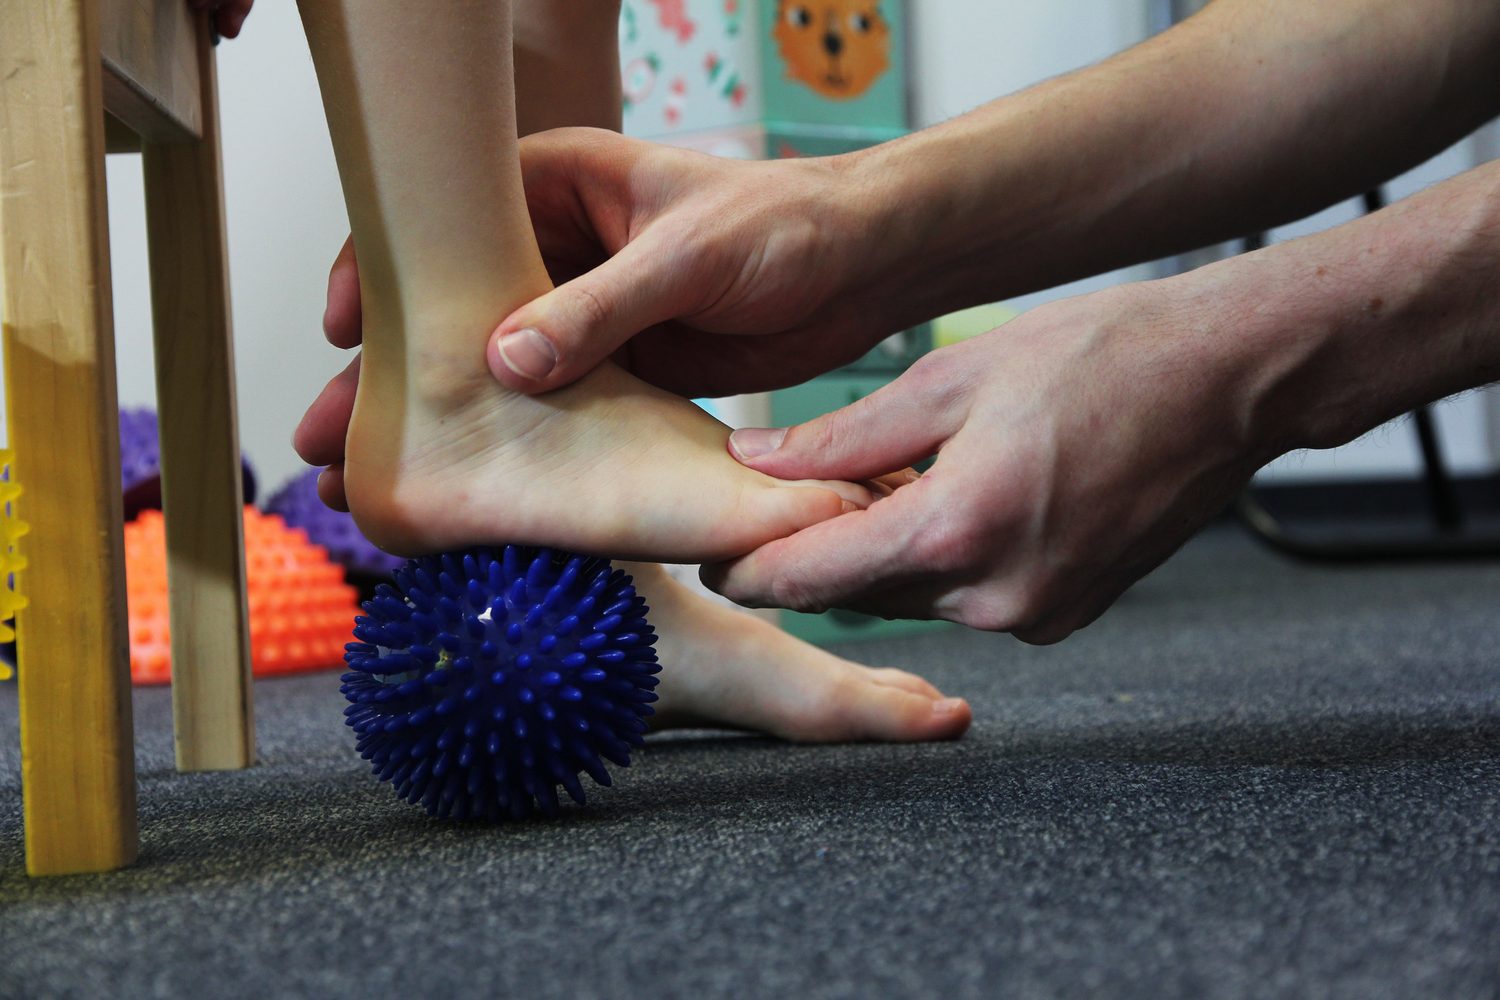
That depends on what type of medical aid you’re addressing with the prosthetist. If it’s orthopaedic insoles or a post-injury limb brace, for example, then the main goal is to wear the aid only for as long as necessary and, thanks to physiotherapy and the client’s proactive approach, improve their condition to the point where they can do without the orthopaedic aid entirely—or wear it only occasionally as needed.
In more complex cases—such as aids for patients after amputation, or clients with severe orthopaedic or neurological conditions—it’s of course true that they can’t manage day-to-day life without an aid, and communication between the client and prosthetist is long-term.
My focus is on children’s limb orthoses, sensomotor and orthopaedic insoles, and the related functional assessment of the feet. A natural extension of these areas is recommending suitable footwear for the client to wear with the aid.

Yes. Last year I started my own practice, which I launched in Luhačovice and more recently also in Vizovice in the Zlín area. In the clinic I work with adult clients as well as children, and the main aim is a comprehensive foot assessment and a tailored plan. The solution might include lifestyle measures, explaining suitable exercises, making custom insoles, or recommending appropriate footwear.
Most often it’s various deformities and pain in the feet, such as bunions, hammer toes, heel spurs, arch pain and calluses.
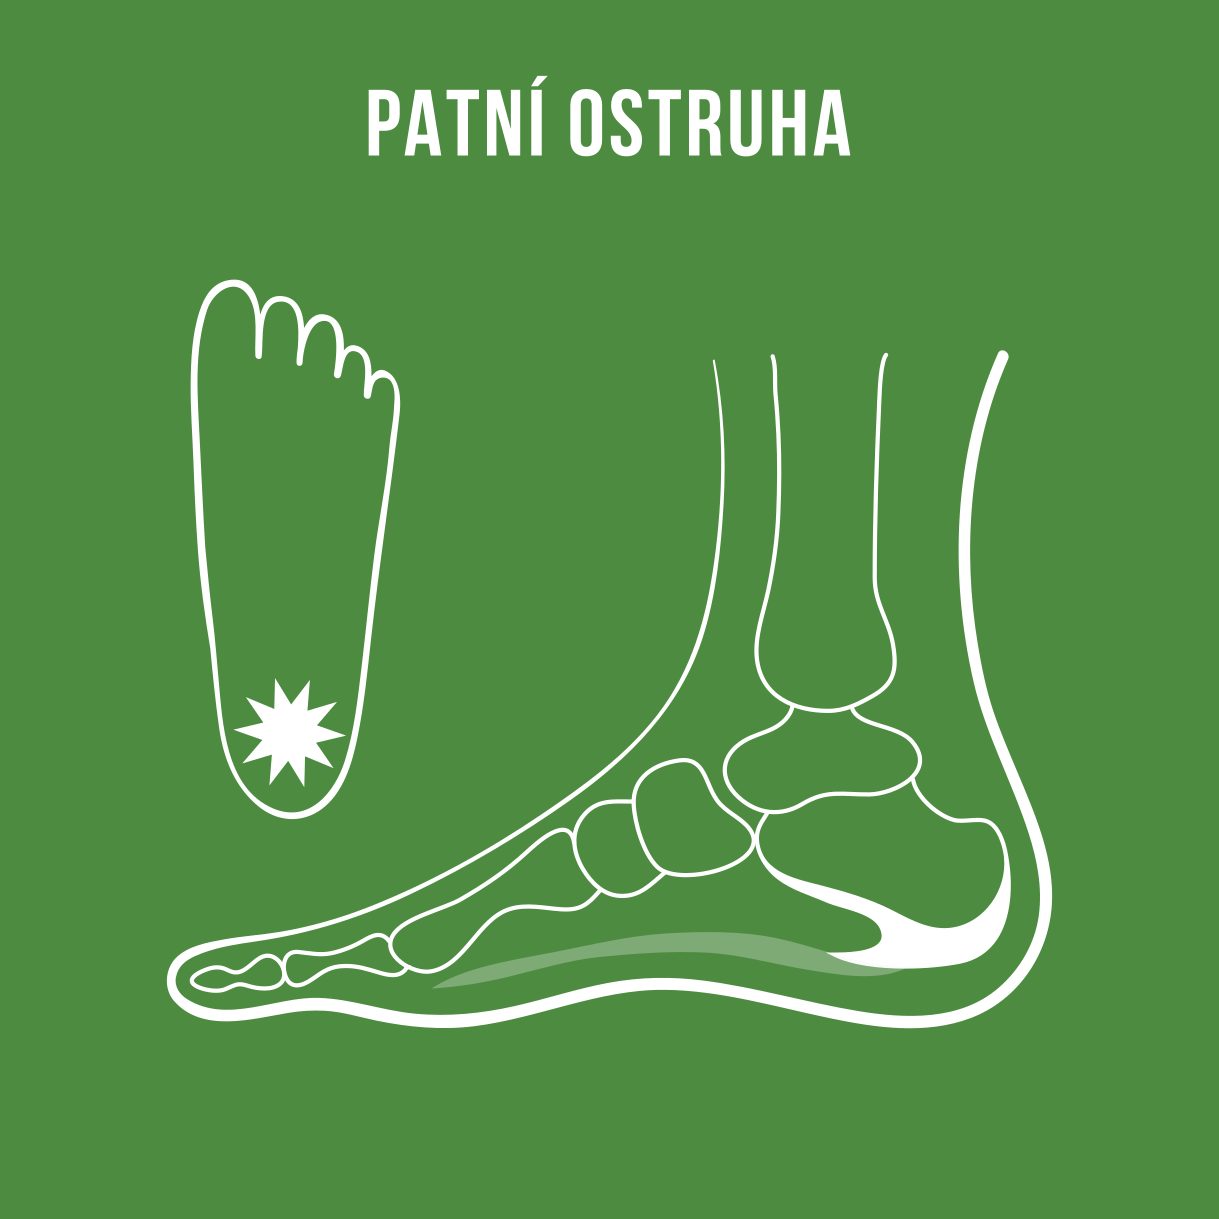
The cause is always individual and depends on many factors that I identify during the assessment. However, the common thread is usually long-term poor habits—we don’t pay our feet any attention over the long term and push them into the background until something starts to hurt. Another important factor that often contributes to foot problems is wearing unsuitable footwear. I address these two points with almost every client.
With children, I most often deal with valgus ankle alignment, poor alignment of the entire lower limbs, flat feet, and so on. I also place a strong emphasis on choosing suitable footwear, which—especially for children—can have a huge impact on healthy foot development. I’d also like to mention that if parents feel something isn’t quite right with their child’s movement, they should seek out a specialist straight away (a doctor, physiotherapist, podiatrist).

I don’t have a simple answer to that. Foot problems (and not only foot problems) are always multifactorial, so there are always several factors behind them that need to be uncovered during the assessment. Then we work with the client on changing and reducing them. But it’s true that one common factor is unsuitable footwear, which in the long term can contribute to a whole range of problems.
Yes. Most orthopaedic aids intended for walking also need to be paired with suitable footwear to work properly. Measurements for making such an orthopaedic aid are usually taken using plaster casting or scanning, and are typically done under load (standing). And that’s where a big problem comes in: afterwards, clients have to figure out what shoes to choose so they can still fit into them with the aid inside.

It can actually be a very good idea. In practice, I really like combining orthopaedic aids with barefoot footwear, because they complement each other brilliantly. If a client has a health issue and needs to wear an aid (insole, brace, etc.), it generally means the aid provides the necessary correction—and the demands on the footwear become narrower overall.
Footwear worn in combination with an orthopaedic aid should be light, flexible and roomy, so the foot fits comfortably even with the aid. Barefoot shoes meet all of these parameters, which is why they can work nicely with orthopaedic aids. Still, it’s always worth discussing this with the technician making the aid, who can recommend suitable footwear for that specific situation.
Compared to conventional shoes, barefoot footwear requires you to pay more attention when walking—monitor your body as you move, adjust your pace and walking style to the surface, and so on. In my view, barefoot shoes don’t forgive much. The most important thing is proper foot function. Shoes are only a kind of outer layer. That’s why I like recommending barefoot footwear to clients whose feet are completely fine, or only have minor deviations.
However, I’m very cautious with recommendations when foot function is impaired and the shoe can’t simply copy the foot without thought. This includes clients with an orthopaedic or neurological condition, significant ankle instability, reduced or increased muscle tone, or more sensitive feet and so on. In these cases, I often pair barefoot footwear with a suitable aid that specifically corrects the issue identified—such as a heel wedge, an insole, or a brace.

It’s probably true that my children are watched more closely than, say, my friends’ children. Sometimes I even have to rein myself in. We try to do exercises, I pay attention to suitable footwear and suitable physical activities, and I’m more bothered by bad habits, and so on. But in my opinion, the only person who can spot a problem in children before it even appears is an experienced paediatric physiotherapist. And that’s not me.
That’s also why I like working with physiotherapists and I refer parents and children to them. I also took my daughter to several physiotherapists—and their advice was invaluable. It moved us forward enormously with our issue, and I’m very grateful for those visits.

The brand that suits me best is LEGUANO. I’ve had great experiences with the GO and HUSKY models, and at the moment I’ve got my eye on the BEAT model. What won me over about LEGUANO was mainly the build quality, low weight and flexibility. Sometimes when I’m walking, I feel like I’m barefoot… like I’m not wearing any shoes at all. It’s quite addictive.

 Bc. Petr Kadlec is anorthotist-prosthetist and podiatrist. In his podiatry clinic he focuses on examining and diagnosing feet, followed by proposing an appropriate solution. During assessments, he also advises clients on choosing suitable footwear. He is based in Luhačovice.
Where to next:


 € - US
 Čeština
 Magyar
 Slovenščina
 Română
 български
 English
 Slovenčina
 Polski
 Dansk
 Nederlands
 Svenska
 Suomi
 Español
 Français
 Português
 Deutsch (DE)
 Deutsch (AT)
 Deutsch (CH)

